
Infantile hemangioma
overview.
The most common tumor of infancy — with a predictable growth curve that makes timing of treatment critical.
Infantile hemangiomas are benign vascular tumors characterized by the proliferation of the endothelial cells.1 These lesions are rarely present at birth, but appear within the first few weeks of a child's life.2
The evolution phases of infantile hemangioma growth include3-5:
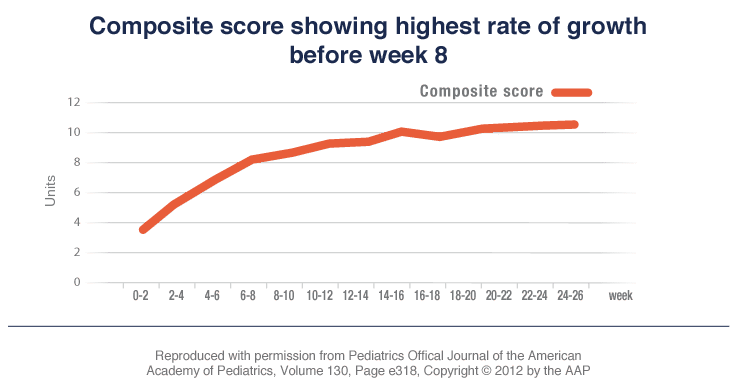
- The proliferation phase: rapid growth between 5 ½ and 7 ½ weeks of age that can last up to 6 months or longer3,4
- The involution phase: stabilization then a slow, spontaneous regression over a span of 3 to 9 years5

10%
of all infants develop an infantile hemangioma — and up to 30% of premature infants.3
5½–7½ wks
of age brings the steepest growth; the proliferation phase can last 6 months or longer.5
~80%
of growth is complete by 3 months of age, narrowing the window for intervention.4
The cause of infantile hemangioma.
It is not well understood what causes infantile hemangiomas. However, studies indicate that fetal hypoxic stress might trigger proliferation and abnormal blood vessel formation by stimulating endothelial progenitor cells.
Another hypothesis is that immature endothelial cells and pericytes, which coexist in the late stages of fetal development, may maintain persistent proliferation properties for a period of time after birth, leading to the development of infantile hemangioma.2
Populations at higher risk5
Diagnosis and treatment.
Early therapeutic intervention during the proliferation phase of hemangioma growth is essential.
Diagnosis of infantile hemangioma requires a physical examination along with review of the patient's medical history, including determining how long the infantile hemangioma has been present and if it has changed. Although IH is often diagnosed on physical examination and medical history alone, in some cases imaging tests can also be helpful.7
It may be important to refer to a specialist, such as a pediatric dermatologist, to help confirm a diagnosis and find the most appropriate treatment for your patient as soon as possible.2 Early treatment during the proliferation phase between 1 month to 5 months is important.3
Physical examination
History and exam — including how long the lesion has been present and whether it has changed — remain the foundation of diagnosis.
MRI
Helps differentiate infantile hemangiomas from other vascular lesions, such as arteriovenous or venous malformations.8
Biopsy with GLUT-1 stain
GLUT-1 is an exclusive marker for IH. Proliferating and involuting hemangiomas stain positively, while other cutaneous vascular neoplasms, malformations, and normal vasculature do not — making the stain highly sensitive and specific for histologic confirmation.9
Types of infantile hemangiomas.
Infantile hemangiomas can be divided into superficial, subcutaneous (deep), and mixed hemangiomas. All types are slightly warm to the touch.5
50%–60% of all IH
Superficial
Often described as “strawberry marks” — a bright red tumor with an irregular surface.
~15% of all IH
Subcutaneous (Deep)
Protruding tumors appearing under normal or bluish skin.
25%–35% of all IH
Mixed
Exhibit a combination of both superficial and subcutaneous characteristics.
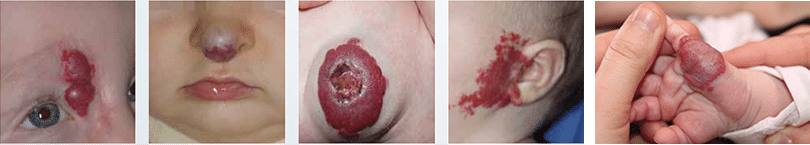
Morphological subtypes of infantile hemangiomas
Focal (localized)1
- Located on the bony prominences
- 60% are located on the head and neck
Multifocal2
- Multiple hemangiomas that can range in number
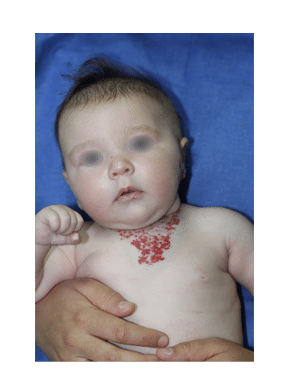
Segmental3
- Cover 1 or more segments of the face and body
- Can grow for up to 2 years
Most infantile hemangiomas are the nodular type, which are discrete, oval or round, and usually not associated with malformations. However, segmental hemangiomas are at a higher risk for complications like frequent ulceration. Segmental hemangiomas may have visceral involvement of internal organs, including the liver, gastrointestinal tract, cardiovascular system and brain.1
Segmental hemangiomas may also be associated with developmental abnormalities, including PHACE syndrome, LUMBAR syndrome (also known as SACRAL syndrome).1
Syndromes associated with segmental hemangiomas
PHACE syndrome
The acronym for PHACE stands for4:
- Posterior fossa anomalies
- Hemangioma
- Arterial lesions
- Cardiac and aortic abnormalities
- Eye abnormalities
About 20% of segmental infantile hemangioma are associated with PHACE syndrome—88% of which are females.1
LUMBAR syndrome
The acronym for LUMBAR stands for1:
- Lower body infantile hemangioma
- Urogenital anomalies
- Myelopathy / spinal cord malformations
- Bony defects
- Anorectal malformations and/or Arterial anomalies
- Renal anomalies
In a study of 11 patients with LUMBAR syndrome, approximately 73% had digestive abnormalities and about 64% had urinary tract abnormalities.5
The classification of vascular anomalies.
There are 2 classifications of vascular anomalies: vascular tumors and vascular malformations.10
Vascular tumors
The most common type of vascular tumor is infantile hemangioma.
Other types of vascular tumors include
- Congenital hemangioma
- Tufted angioma
- Kaposiform hemangioendothelioma
- Spindle cell hemangioendotheliomas
- Epithelioid hemangioma
- Hemangioendotheliomas
- Others
Vascular malformations
Simple
- Capillary malformation (CM)
- Venous malformation (VM)
- Lymphatic malformation (LM)
- Arteriovenous malformations
- Arteriovenous fistula
Combined vascular malformations
- Capillary venous malformation (CVM)
- Capillary lymphatic malformation (CLM)
- Capillary-arteriovenous malformation (CAVM)
- Lymphatic-venous malformation (LVM)
- Capillary-lymphatic-venous malformation (CLVM)
- Capillary-lymphatic-arteriovenous malformation (CLAVM)
- Capillary-venous-arteriovenous malformation (CVAVM)
- Capillary-lymphatic-venous-arteriovenous malformation (CLVAVM)
Anomalies of major named vessels
Anomalies of
- Origin
- Course
- Number
- Length
- Diameter
- Communication (AVF)
- Persistence (of embryonal vessels)
Associated with other anomalies
- Klippel-Trenaunay syndrome
- Parkes Weber syndrome
- Servelle-Martorell syndrome
- Sturge-Weber syndrome
- Limb CM + congenital non-progressive limb hypertrophy
- Maffucci syndrome
- Macrocephaly
- CLOVES syndrome
- Proteus syndrome
- Bannayan-Riley-Ruvalcaba syndrome
Vascular tumors grow mainly by endothelial cell hyperplasia, whereas vascular malformations have a quiescent endothelium and are considered localized defects of vascular morphogenesis.11
While vascular tumors can regress or persist depending on type, vascular malformations persist throughout a child’s life and never regress. Most vascular malformations have commensurate growth during childhood, and some worsen over time if left untreated.11
For help in differentiating vascular tumors from vascular malformations, refer to a specialist. A pediatric dermatologist can help determine a proper diagnosis and find the appropriate treatment.
The Serious Impact of Infantile Hemangiomas on Patients and Their Caregivers
Infantile hemangiomas are the most common benign tumors of infancy—affecting up to 10% of all infants and up to 30% of premature babies.12 Among these infants, about 12% have complications that lead to ulceration, impaired vision, or disfigurement.13
Serious complications of infantile hemangiomas include12,14:
- Permanent harm to a child’s vision
- Auditory canal obstruction
- Painful ulceration
For every 10 cm² increase in the size of a hemangioma, there is an approximately 5% increase in complications.14
1/3
of facial infantile hemangiomas will result in soft tissue distortion or damage14
69%
of infantile hemangiomas leave residual lesions when left untreated15
Infantile hemangiomas may also cause long-lasting psychological effects on parents and caregivers and later on the affected children.
Ready to learn more about treatment?
About HEMANGEOL: Efficacy & Safety →References
- 1.Léauté-Labrèze C, Prey S, Ezzedine K. Infantile haemangioma: part I. Pathophysiology, epidemiology, clinical features, life cycle and associated structural abnormalities. J Eur Acad Dermatol Venereol. 2011;1-9. [epub ahead of print]
- 2.Hemangioma Investigator Group website. Multiple hemangiomas. https://hemangiomaeducation.org/info_multiple.html. Accessed February 28, 2014.
- 3.Vascular Birthmark Institute website. Hemangiomas – Segmental. https://www.vbiny.org/photo-gallery/hemangiomas/segmental. Accessed February 10, 2014.
- 4.Tollefson MM, Frieden IJ. Early growth of infantile hemangiomas: what parents’ photographs tell us. Pediatrics. 2012;130(2):e314-e320.
- 5.Girard C, Bigorre M, Guillot B, Bessis D. PELVIS syndrome. Arch Dermatol. 2006;142:884-888.
- 7.American Academy of Orthopaedic Surgeons website. Hemangioma.
- 8.Antaya RJ. Infantile hemangioma. 2007:1-20.
- 9.Lowe LH, Marchant TC, Rivard DC, Scherbel AJ. Vascular malformations: classification and terminology the radiologist needs to know.
- 10.ISSVA classification for vascular anomalies. https://www.issva.org/content.aspx?page_id=22&club_id=298433&module_id=152904. Accessed June 9, 2014.
- 11.Enjolras O, Wassef M, Chapot R. Introduction: ISSVA classification. Cambridge University Press website. Accessed February 28, 2014.
- 12.Storch CH, Hoeger PH. Propranolol for infantile haemangiomas: insights into the molecular mechanisms of action. Br J Dermatol. 2010;163:269–274.
- 13.Drolet BA, Frommelt PC, Chamlin SL, et al. Initiation and use of propranolol for infantile hemangioma: report of a consensus conference. Pediatrics. 2013;131(1):128-140.
- 14.Haggstrom AN, Drolet BA, Baselga E, et al. Prospective study of infantile hemangiomas: clinical characteristics predicting complications and treatment. Pediatrics. 2006;118(3):882-888.
- 15.Bauland CG, Lüning TH, Smit JM, Zeebregts CJ, Spauwen PHM. Untreated hemangiomas: growth pattern and residual lesions. Plast Reconstr Surg. 2011:127(4):1643-1648.
- 16.Tollefson MM, Frieden IJ. Early growth of infantile hemangiomas: what parents’ photographs tell us. Pediatrics. 2012;130(2):e314-e320.